
Sinus infection symptoms affect over thirty million adults annually, turning common nasal congestion into persistent facial throbbing, heavy head pressure, and exhausting fatigue. While most sinus inflammation begins as a self-limiting viral cold, swelling inside the narrow drainage channels of the skull can trap fluid, creating an environment where secondary bacterial infections develop.
Understanding the exact symptoms of a sinus infection helps patients distinguish between routine seasonal allergies, viral rhinosinusitis, and true bacterial sinus infections requiring targeted medical therapy. Recognizing which sinus cavities are inflamed enables clearer communication with healthcare providers and prevents the premature or unnecessary use of prescription antibiotics.
Key Takeaways & Clinical Summary
- Over ninety percent of acute sinus infections are viral and resolve naturally within seven to ten days without prescription antibiotics.
- Bacterial sinusitis is diagnosed primarily when symptoms persist past ten consecutive days without improvement, or when a patient experiences the classic double sickening pattern.
- Facial pain location correlates directly with the involved sinus chamber: forehead tenderness indicates frontal sinusitis, upper teeth pain points to maxillary involvement, and deep eye pressure suggests ethmoid or sphenoid inflammation.
- Nasal irrigation with sterile or distilled water provides rapid mechanical clearing of thick secretions while avoiding rare microbial contamination risks.
- Over-the-counter topical nasal sprays containing oxymetazoline must not be used beyond three consecutive days to prevent severe rebound congestion known as rhinitis medicamentosa.
Anatomical Overview: The Four Paranasal Sinus Cavities
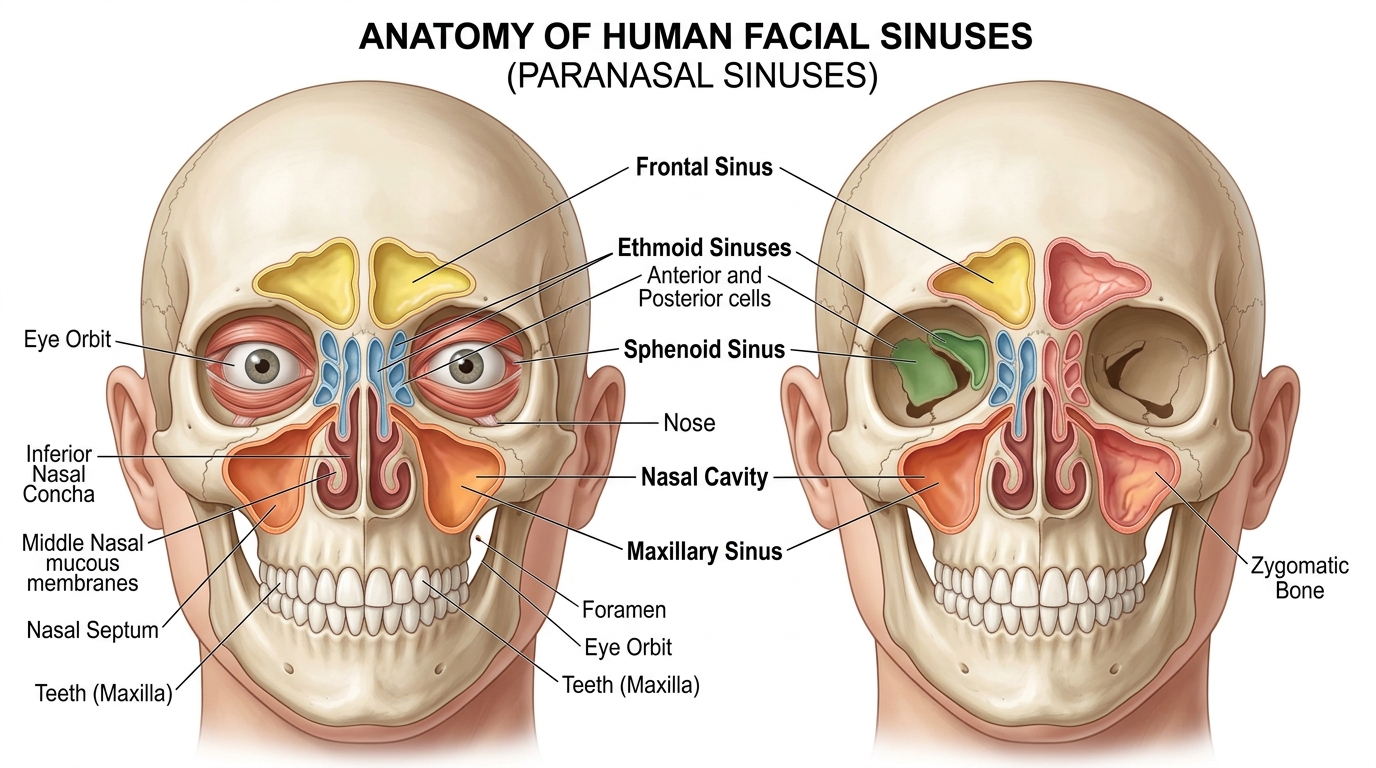
The human skull contains four paired, air-filled cavities known as the paranasal sinuses. These chambers lighten the weight of the head, humidify inhaled air, and contribute to vocal resonance. Each sinus cavity connects to the nasal passages through microscopic openings called ostia, which are lined with microscopic hair-like structures called cilia that continually sweep mucus outward.
When viral upper respiratory infections or allergens trigger mucosal swelling, the ostia become blocked. Mucus accumulates, oxygen levels inside the chamber decrease, and mucosal pressure builds rapidly. The specific symptoms an individual feels depend heavily on which anatomical chambers are congested:
- Maxillary Sinuses (Cheeks): Located behind the cheekbones beneath the eye sockets. Infection here produces intense pain across the cheekbones, tenderness under the eyes, and referred ache in the upper molar teeth because dental nerve roots sit immediately below the sinus floor.
- Frontal Sinuses (Forehead): Situated above the eyebrows in the frontal bone of the forehead. Inflammation causes severe frontal headaches that typically intensify when bending forward or lying completely flat.
- Ethmoid Sinuses (Between the Eyes): Composed of a honeycomb network of small air cells situated between the bridge of the nose and the inner eye corners. Infection causes tenderness across the bridge of the nose, swollen eyelids, and pain radiating between the eyes.
- Sphenoid Sinuses (Deep Skull Base): Resting deep behind the ethmoid sinuses near the optic nerve and pituitary gland. Sphenoid sinusitis causes deep, generalized head pressure often described as pain at the top or vertex of the head or behind the neck.
| Sinus Cavity | Primary Pain Location | Associated Symptoms | Common Aggravating Factors |
|---|---|---|---|
| Maxillary | Cheeks, upper jaw, teeth | Dental ache, cheek swelling, facial tenderness | Chewing, head tilted downward |
| Frontal | Forehead, above eyebrows | Throbbing supraorbital headache, light sensitivity | Bending forward, lying supine |
| Ethmoid | Between eyes, nasal bridge | Periorbital pressure, tearing, loss of smell | Eye movement, nasal pressure |
| Sphenoid | Vertex of skull, back of head | Deep retro-orbital pain, neck stiffness, dizziness | Changes in altitude, recumbency |
Clinical Differentiation: Viral vs. Bacterial Sinusitis
The single greatest clinical challenge in managing sinus complaints is determining whether an infection is caused by a respiratory virus (such as rhinovirus, influenza, or respiratory syncytial virus) or a secondary bacterial invasion (typically Streptococcus pneumoniae, Haemophilus influenzae, or Moraxella catarrhalis). Because viral and bacterial infections initially present with identical symptoms, clinical diagnosis relies on strict time-based criteria established by medical societies.
Clinicians evaluate three primary diagnostic markers to differentiate bacterial from viral disease:
- The 10-Day Duration Rule: Viral upper respiratory symptoms peak within three to five days and progressively improve by day seven to ten. If nasal obstruction, discolored discharge, and facial pressure persist past ten consecutive days without any sign of clinical improvement, bacterial sinusitis is suspected.
- The Double Sickening Phenomenon: A patient catches a common cold, begins to recover over four to five days, and then abruptly experiences worsening fever, intensified facial pain, and heavier nasal secretions. This secondary drop in clinical status strongly suggests bacterial colonization of stagnant sinus mucus.
- Severe Initial Presentation: Symptoms that begin with high fever (above 102 degrees Fahrenheit or 39 degrees Celsius), severe unremitting facial pain, and thick purulent nasal discharge that persist for at least three to four consecutive days at the very onset warrant prompt clinical evaluation.
Contrary to widespread belief, the color of nasal discharge alone (whether clear, yellow, or green) does not prove a bacterial infection. White blood cells fighting a routine viral cold naturally produce myeloperoxidase enzymes that turn mucus yellow or dark green during normal immune clearance.

Recovery Timelines: Acute, Subacute & Chronic Stages
Sinus infections are classified medically based on symptom duration and recurrence frequency. Tracking where an illness falls along this clinical continuum guides treatment choices and identifies when advanced diagnostic imaging is needed:
- Acute Rhinosinusitis (Less than 4 Weeks): Characterized by sudden onset of nasal blockage, purulent rhinorrhea, and facial pressure. The vast majority of acute episodes resolve completely within ten to fourteen days with conservative symptomatic care.
- Subacute Rhinosinusitis (4 to 12 Weeks): Represents an intermediate stage where low-grade inflammation or persistent bacterial presence fails to clear completely after initial treatment. Symptoms are often less intense but cause ongoing post-nasal drip, morning cough, and mild nasal blockage that frequently triggers chronic nighttime snoring due to compromised nasal airflow.
- Chronic Rhinosinusitis (12 Weeks or Longer): Defined as continuous sinus inflammation lasting three months or more despite medical therapy. Chronic cases are frequently driven by anatomical obstruction, non-allergic tissue hyperreactivity, persistent nasal polyps, or bacterial biofilm formation rather than active acute infection.
- Recurrent Acute Rhinosinusitis: Diagnosed when a patient experiences four or more separate acute sinus infection episodes within a single calendar year, with complete resolution of symptoms between flare-ups.
Over-the-Counter Care, Decongestants & Medication Safety
Relieving sinus infection discomfort requires a systematic combination of thinning thick mucus, shrinking swollen lining tissue, and controlling inflammatory pain. However, improper use of over-the-counter remedies can lead to significant complications:
- Topical Nasal Steroids (Fluticasone, Mometasone, Budesonide): Considered the gold-standard anti-inflammatory treatment for both viral and bacterial sinusitis. Daily use reduces swollen mucous membranes and opens blocked sinus ostia. For maximum effectiveness, angle the spray nozzle slightly outward toward the ear rather than straight up the nasal septum to prevent nosebleeds.
- Oral Mucolytics (Guaifenesin): Increases hydration within the respiratory tract, thinning viscous secretions so that natural cilia can expel trapped mucus from the sinus cavities. Optimal results require drinking substantial water alongside medication.
- Topical Decongestant Sprays (Oxymetazoline, Phenylephrine): Provide fast-acting vasoconstriction that opens clogged nasal passages within minutes. Crucially, these sprays must never be used for more than three consecutive days. Extended use causes rebound mucosal swelling and severe physical dependency known as rhinitis medicamentosa.
- Oral Decongestants (Pseudoephedrine): Effective systemic vasoconstrictors available behind pharmacy counters. Patients with hypertension, cardiovascular disease, thyroid disorders, or glaucoma should consult a physician before use because pseudoephedrine improves heart rate and blood pressure.
- Systemic Analgesics (Acetaminophen, Ibuprofen): Target facial headache, toothache, and fever. Non-steroidal anti-inflammatory drugs (NSAIDs) like ibuprofen also assist in reducing localized tissue swelling around sinus ostia.
Nasal Irrigation Protocols & Distilled Water Safety
Nasal saline irrigation using squeeze bottles or neti pots is one of the most effective, evidence-backed non-pharmacological therapies for acute and chronic sinus symptoms. Flushing the nasal passages physically washes away stagnant crusting, allergens, and inflammatory cytokines while rehydrating delicate mucosal membranes.
Strict safety precautions are required when performing nasal irrigation to avoid life-threatening waterborne infections:
- Never Use Untreated Tap Water: Tap water contains low levels of harmless microbes when swallowed, but delicate nasal tissues offer a direct pathway to the skull base. Rare amoebic infections, notably Naegleria fowleri, enter through the cribriform plate and cause fatal primary amebic meningoencephalitis.
- Safe Water Sources: Always prepare saline rinses using commercially purchased distilled water, sterile water, or tap water that has been boiled vigorously for at least three to five minutes and cooled completely to room temperature.
- Device Hygiene: Clean irrigation bottles with hot soapy water after each use and allow them to air dry thoroughly. Replace irrigation containers every three months to prevent bacterial biofilm colonization.
- Proper Head Positioning: Lean forward over a sink at a forty-five-degree angle, breathe through the mouth, and introduce the solution gently. Avoid forceful squeezing, which can drive fluid into the middle ear through the eustachian tube.
Antibiotic Stewardship & Prescription Pathways
When clinical criteria confirm acute bacterial rhinosinusitis, targeted prescription antibiotic therapy aims to eradicate pathogenic bacteria and prevent chronic complications. Medical guidelines emphasize responsible antibiotic stewardship to limit gastrointestinal side effects, drug-resistant bacterial strains, and secondary complications such as oral thrush fungal overgrowth.
First-line therapy for non-allergic adults is oral amoxicillin-clavulanate (Augmentin) for five to seven days, which provides broad coverage against beta-lactamase-producing bacteria. For patients with documented penicillin allergies, clinicians typically prescribe oral doxycycline or respiratory fluoroquinolones such as levofloxacin, which occasionally require monitoring of liver function on an AST blood test during extended therapy.
Macrolide antibiotics like azithromycin (Z-Pak) are no longer recommended as primary treatments for acute bacterial sinusitis due to high rates of bacterial resistance among Streptococcus pneumoniae strains in the United States and Europe.
Pediatric Considerations: Sinusitis in Toddlers & Children
Diagnosing sinus infection symptoms in pediatric patients requires careful clinical evaluation because children under age seven have incompletely developed sinus cavities. Maxillary and ethmoid sinuses are present at birth, but frontal and sphenoid sinuses do not develop until late childhood and adolescence.
In toddlers and young children, acute sinusitis rarely presents with classic adult complaints like localized forehead throbbing. Instead, parents and caregivers should observe for these signs:
- A persistent daytime cough lasting longer than ten consecutive days that worsens when lying down.
- Continuous thick yellow or green nasal discharge accompanied by low-grade fever and irritability.
- Noticeable puffiness, dark circles, or mild swelling around one or both eyes upon waking.
- Unexplained bad breath (halitosis) in a young child who does not have dental decay or a pharyngeal foreign object.
Red Flag Emergency Symptoms & Complications
While the vast majority of sinus infections resolve without incident, the close proximity of the paranasal sinuses to the brain, orbits, and major blood vessels means untreated severe bacterial infections can spread. Seek emergency medical evaluation immediately if any of the following critical warning signs appear:
- Periorbital or Orbital Cellulitis: Redness, marked swelling, pain, or bulging (proptosis) of the eye, drooping eyelid, or inability to move the eyeball freely.
- Visual Changes: Sudden double vision (diplopia), blurred vision, or decreased visual acuity.
- Intracranial Complications: Severe unremitting headache unresponsive to pain medication, neck stiffness (meningismus), high fever, confusion, or marked lethargy.
- Forehead Swelling (Pott Puffy Tumor): A soft, doughy swelling on the forehead caused by osteomyelitis of the frontal bone secondary to frontal sinusitis.
Advanced Diagnostic & Surgical Options
For individuals with persistent chronic rhinosinusitis or recurrent acute infections that fail multiple rounds of medical management, an otolaryngologist (ENT specialist) performs diagnostic procedures to identify structural causes:
- Nasal Endoscopy: A gentle in-office examination utilizing a thin, illuminated fiber-optic scope to directly inspect the sinus drainage pathways, evaluate for nasal polyps, and collect targeted bacterial cultures.
- High-Resolution Sinus CT Scan: Detailed cross-sectional imaging that reveals anatomical obstructions, bone thickening, mucociliary blockages, and silent fluid levels inside all four sinus pairs.
- In-Office Balloon Sinuplasty: A minimally invasive procedure where a small balloon catheter is inserted into narrowed sinus ostia and dilated, gently remodeling the bone framework to restore permanent natural drainage without tissue cutting.
- Functional Endoscopic Sinus Surgery (FESS): An outpatient surgical intervention performed under general anesthesia to remove diseased tissue, excise obstructing polyps, and widen natural drainage pathways.
- Biologic Therapies: Monoclonal antibody medications (such as dupilumab or omalizumab) targeted for patients with severe chronic rhinosinusitis with nasal polyps driven by type 2 inflammatory pathways.
Frequently Asked Questions
How can I tell if my sinus infection is bacterial or viral?
Viral sinus infections usually peak within three to five days and resolve within ten days. Bacterial infections either persist past ten consecutive days without improvement, worsen abruptly after initial recovery (double sickening), or present with severe high fever and intense facial pain from day one.
Why does my upper jaw and teeth hurt during a sinus infection?
The roots of your upper molar and premolar teeth extend directly into the floor of the maxillary sinus cavity. When fluid and pressure accumulate inside the maxillary sinus, swelling presses down on surrounding dental nerves, causing referred toothache.
Is a sinus infection contagious to other people?
The sinus infection itself is not contagious. However, the initial respiratory viruses that triggered the mucosal swelling (such as rhinovirus or influenza) are easily transmitted through airborne droplets and surface contact.
Why is it dangerous to use tap water in a neti pot or nasal rinse?
Municipal tap water contains harmless microscopic organisms when ingested, but delicate nasal tissues offer a direct channel to the brain. Rare amoebas like Naegleria fowleri can cause fatal brain infections if unboiled tap water is introduced into nasal passages. Always use distilled or boiled water.
How long can I safely use over-the-counter nasal decongestant spray?
Topical decongestant sprays containing oxymetazoline should never be used for more than three consecutive days. Prolonged use causes severe rebound nasal congestion known as rhinitis medicamentosa, leading to physical tissue dependency.
Does green or yellow mucus always mean I need antibiotics?
No. Nasal mucus naturally turns yellow or dark green during routine viral colds because white blood cells produce colored enzymes while clearing viral particles. Mucus color alone does not indicate bacterial infection.
Can I fly on an airplane with a sinus infection?
Flying with active sinus blockage can cause severe facial barotrauma, severe headaches, and eustachian tube dysfunction due to rapid cabin pressure shifts. If travel is unavoidable, use oral decongestants and saline rinses thirty minutes prior to descent.
What are the red flag symptoms that require emergency medical care?
Seek emergency care immediately if you experience eye swelling, double vision, inability to move the eye, severe unyielding headache with neck stiffness, high fever with mental confusion, or localized swelling on the forehead.
When should I consult an ear, nose, and throat (ENT) specialist?
You should consult an ENT specialist if your sinus symptoms last longer than twelve weeks, if you experience four or more acute episodes per year, or if standard prescription antibiotic treatments fail to resolve symptoms.
