
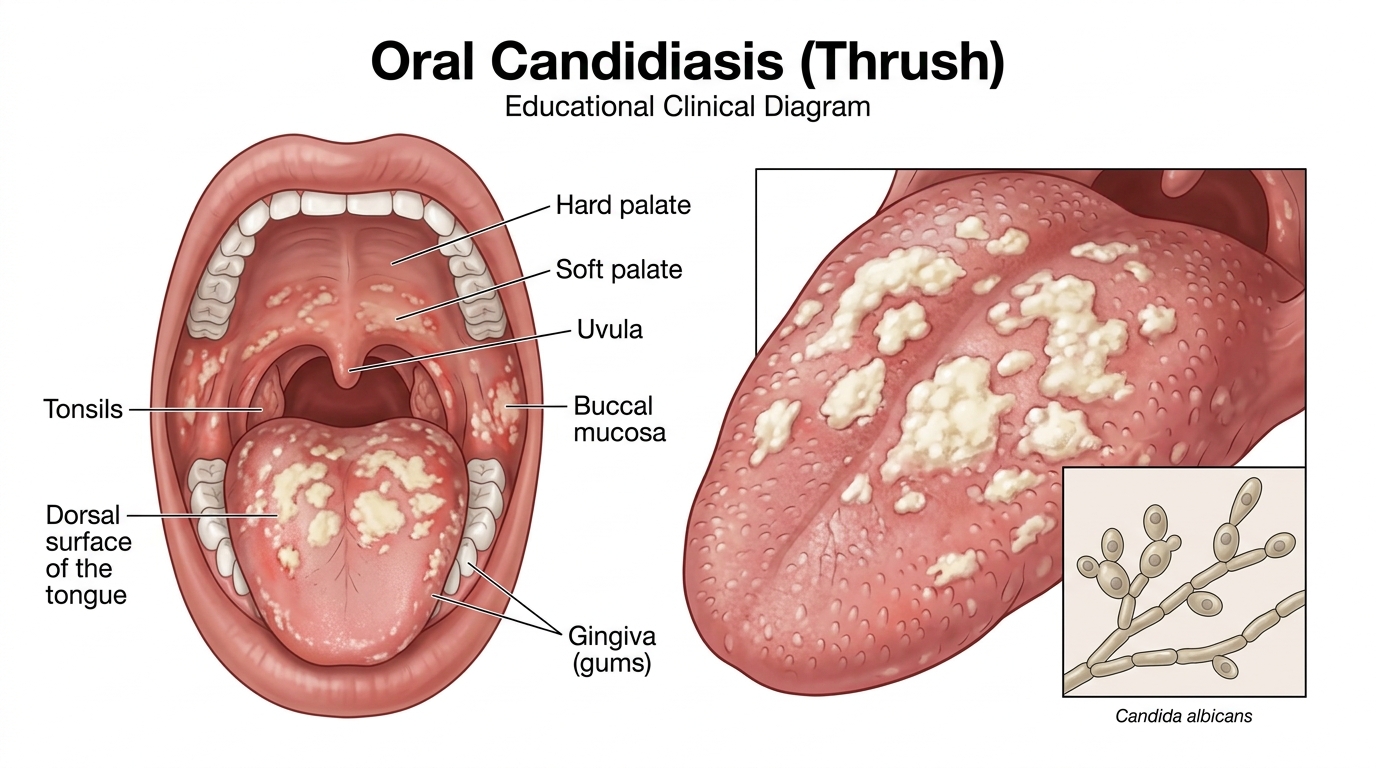
Thrush in mouth, known clinically as oral candidiasis, is an opportunistic fungal infection of the oral mucous membranes. It occurs when normal microscopic balances inside the mouth are disrupted, allowing the yeast-like fungus Candida albicans to multiply uncontrollably. While Candida is a benign, naturally occurring resident of the human oral microbiome in up to sixty percent of healthy individuals, specific triggers can transform this harmless commensal organism into an invasive, symptomatic infection.
The infection typically manifests as thick, creamy white plaques coating the dorsal surface of the tongue, the inner cheeks, the roof of the mouth, or the gums. Recognizing the early triggers of oral thrush, understanding its multiple clinical variants, and following evidence-based treatment protocols allows patients to resolve discomfort quickly while identifying underlying metabolic or immune triggers.
Because oral fungal overgrowth can coincide with upper respiratory or immune challenges, clinicians often evaluate patient symptoms alongside sinus infection symptoms or review liver function using an AST blood test when administering systemic antifungal medications.
Key Takeaways & Clinical Summary
- Oral thrush is caused by the fungal yeast Candida albicans exploiting temporary shifts in immune function, salivary flow, or bacterial competition.
- A classic hallmark of pseudomembranous thrush is white cottage-cheese-like plaques that can be gently scraped away, revealing a bright red, raw, and tender mucosal base underneath.
- Common medication triggers include inhaled corticosteroids used for asthma or COPD without a spacer, and broad-spectrum oral antibiotics that eradicate protective beneficial oral bacteria.
- Denture wearers are particularly susceptible to denture stomatitis, requiring rigorous mechanical cleaning and overnight non-bleach disinfection to prevent fungal biofilm recolonization.
- Prescription topical antifungals (Nystatin suspension or Clotrimazole troches) or systemic tablets (Fluconazole) remain the definitive curative therapy, supported by gentle saline rinses and dietary adjustments.
Clinical Variants of Oral Candidiasis
Oral candidiasis does not always look like classic white patches. Oral medicine specialists recognize four distinct clinical presentations, each with unique diagnostic appearances and therapeutic implications:
- Pseudomembranous Candidiasis (Classic Thrush): The most recognizable form, accounting for roughly thirty-five percent of cases. Characterized by creamy white or yellowish curdy lesions resembling cottage cheese on the tongue, buccal mucosa, palate, and labial surfaces. Scraping the surface dislodges the fungal membrane, leaving an erythematous, bleeding base.
- Erythematous (Atrophic) Candidiasis: Often called "antibiotic sore mouth." It lacks the white pseudomembrane entirely, presenting instead as smooth, depapillated, fiery-red patches on the dorsum of the tongue or the hard palate. Patients report intense burning sensations, especially when consuming acidic or spicy foods.
- Hyperplastic Candidiasis (Candidal Leukoplakia): A firmer, chronic variant presenting as confluent, hard white plaques on the lateral borders of the tongue or anterior cheeks that cannot be easily scraped off. This form requires clinical biopsy because chronic hyperplastic lesions carry a small risk of epithelial dysplasia.
- Angular Cheilitis (Perlèche): Deep, painful erythematous fissures, maceration, and crusting at the bilateral commissures (corners) of the mouth. Often driven by mixed fungal-bacterial infection (Candida albicans combined with Staphylococcus aureus), frequently aggravated by saliva pooling due to ill-fitting dentures or facial skin folding.
| Clinical Type | Visual Presentation | Common Symptoms | Frequent Triggers |
|---|---|---|---|
| Pseudomembranous | White, creamy curd-like plaques | Cottony feeling, altered taste, bleeding when scraped | Infancy, steroid inhalers, immunosuppression |
| Erythematous | Fiery red, smooth patches without white plaques | Severe burning, stinging with hot or spicy foods | Recent broad-spectrum antibiotics, dry mouth |
| Angular Cheilitis | Cracked, bleeding fissures at mouth corners | Pain on opening mouth, crusting, cracking | Saliva pooling, denture wear, B12/iron deficiency |
| Hyperplastic | Hard, adherent white plaques that do not scrape away | Mild chronic roughness, tongue stiffness | Chronic tobacco use, poor denture hygiene |
Primary Triggers & Pathophysiology
The transformation of Candida from a harmless resident into an aggressive pathogen requires an ecological breakdown in the host mouth. The primary clinical mechanisms driving this overgrowth include:
- Broad-Spectrum Antibiotic Therapy: Antibiotics frequently prescribed for acute sinus infection symptoms, such as amoxicillin and cephalosporins, indiscriminately destroy protective oral commensal bacteria (such as Streptococcus viridans). Without competitive bacterial inhibition, fungal spores proliferate unchecked.
- Inhaled Corticosteroids: Daily inhalers prescribed for asthma and chronic obstructive pulmonary disease (COPD), such as fluticasone, budesonide, or beclomethasone, deposit microscopic steroid residues on the tongue and soft palate. Local steroid deposition suppresses mucosal salivary IgA antibodies and impairs local phagocyte activity.
- Impaired Salivary Flow (Xerostomia): Saliva contains antifungal proteins including histatins, lactoferrin, and lysozyme that naturally regulate fungal populations. Dehydration, Sjögren syndrome, head and neck radiation therapy, or medications (antihistamines, antidepressants, diuretics) that induce severe dry mouth strip away this protective biological barrier.
- Uncontrolled Diabetes Mellitus: Elevated blood glucose concentrations increase glucose levels within salivary secretions. Candida yeast feeds directly on simple carbohydrates, fueling rapid proliferation and biofilm formation on oral tissues, a metabolic disruption often seen alongside metabolic fatty liver disease and insulin resistance.
- Cell-Mediated Immunodeficiency: T-lymphocytes are the primary immune defense against fungal invasion. Chemotherapy, chronic oral prednisone use, organ transplant immunosuppression, or advanced HIV infection drastically increase vulnerability to severe candidiasis.
Denture Stomatitis & Prosthetic Hygiene Protocols
Among older adults, full or partial removable dentures represent the single most common cause of persistent oral candidiasis. The micro-environment underneath a maxillary acrylic denture is warm, moist, acidic, and shielded from the cleansing flow of saliva, creating ideal conditions for fungal proliferation.
Candida albicans forms dense, protective biofilms within the microscopic pores of polymethyl methacrylate acrylic. If denture wearers treat only their oral tissues with medication while continuing to wear contaminated dentures, the prosthesis acts as a permanent fungal reservoir, causing rapid re-infection.
To break this cycle, patients must follow a rigorous prosthetic decontamination protocol:
- Never Sleep with Dentures in Place: Remove dentures for at least six to eight hours each night to allow oral mucosa to breathe and re-establish natural salivary contact.
- Mechanical Scrubbing: Clean all prosthetic surfaces twice daily with a dedicated denture brush and mild non-abrasive soap. Avoid standard toothpaste, which contains abrasive particles that scratch acrylic and create microscopic crevices for fungal colonization.
- Antifungal Soaking: Soak acrylic dentures overnight in a non-chlorine antifungal disinfectant solution or an effervescent alkaline peroxide cleanser. For full acrylic dentures without metal clasps, a dilute sodium hypochlorite soak (one part household bleach to ten parts water for fifteen minutes, followed by thorough rinsing) eradicates fungal spores.
- Topical Treatment of the Palate: Apply prescribed antifungal cream directly to the tissue-contact surface of the denture before inserting it during active therapy.
Medical Management & Antifungal Pharmacotherapy
Resolving active oral candidiasis requires targeted antifungal pharmacotherapy prescribed by a physician or dentist. Treatment regimens are divided into topical and systemic options based on infection severity and patient immune status:
- Topical Nystatin Oral Suspension (100,000 U/mL): The traditional first-line topical therapy for mild, uncomplicated thrush in both adults and infants. Patients swish four to six milliliters in the mouth for several minutes to ensure prolonged mucosal contact before swallowing, four times daily for seven to fourteen days.
- Clotrimazole Troches (10 mg): Dissolvable oral lozenges that dissolve slowly in the mouth five times daily. Troches deliver high local drug concentrations directly to affected oral tissues with minimal systemic absorption.
- Systemic Fluconazole (Diflucan): An oral triazole antifungal tablet prescribed for moderate to severe candidiasis, cases unresponsive to topical agents, or immunocompromised individuals. Standard adult dosing begins with a 200 mg loading dose on day one, followed by 100 to 200 mg daily for seven to fourteen days.
- Critical Drug Interactions with Fluconazole: Fluconazole is a potent inhibitor of hepatic cytochrome P450 enzymes (CYP2C9 and CYP3A4). It significantly increases blood concentrations of warfarin (greatly improving bleeding risk) and statin cholesterol medications (increasing rhabdomyolysis risk). Healthcare providers must review all concurrent medications before prescribing systemic fluconazole.
Mother-Infant Dyadic Breastfeeding Coordination
Oral thrush is extremely common in healthy newborns and infants under six months of age due to an immature immune system and a developing oral microbiome. However, when an infant develops thrush while breastfeeding, the infection frequently transfers to the mother's nipples and areolae, causing maternal mammary candidiasis.
Symptoms in the nursing mother include severe, shooting nipple pain during and after feeds, bright pink or shiny areolar skin, and painful cracking that does not heal with routine lanolin creams. If only the baby or only the mother is treated, the fungal infection bounces back and forth in an endless ping-pong cycle.
Successful management requires coordinated dyadic care:
- Simultaneous Treatment: The infant receives oral nystatin suspension dropped gently along the inner cheeks, while the mother applies prescription topical antifungal cream (such as miconazole or clotrimazole) to the nipples immediately after every nursing session.
- Sterilization Protocols: Boil all bottle nipples, pacifiers, teething toys, and breast pump parts in water for twenty minutes daily to kill fungal spores.
- Avoid Storing Expressed Milk: Pumping and freezing breast milk during active candidiasis does not kill Candida spores; using that milk weeks later can reintroduce the infection to the baby.
Differential Diagnosis: Distinguishing Thrush from Other Oral Lesions
Multiple non-fungal oral conditions present with white or red lesions that mimic thrush in mouth. Accurate clinical differentiation prevents inappropriate antifungal use and ensures timely diagnosis of potentially serious mucosal diseases:
| Condition | Can It Be Scraped Off? | Key Diagnostic Features | Clinical Significance |
|---|---|---|---|
| Oral Thrush | Yes (Leaves red, bleeding base) | Curdy white plaques, responsive to antifungals | Benign opportunistic fungal overgrowth |
| Oral Leukoplakia | No (Firmly adherent) | Smooth or rough white patch, painless, tobacco link | Potentially premalignant; requires clinical biopsy similar to suspicious skin cancer lesions on the face |
| Geographic Tongue | No | Red smooth areas with elevated white/yellow borders that migrate | Benign inflammatory condition, non-infectious |
| Oral Lichen Planus | No | Lacy white reticular lines (Wickham striae) on buccal mucosa | Chronic autoimmune T-cell mediated condition |
| Aphthous Ulcer | No (True cratered ulcer) | Single or few discrete round ulcers with red inflammatory halo | Common non-contagious canker sores |
Evidence-Based Supportive Home Care & Dietary Guidelines
While prescription antifungal medications remain necessary to eradicate established fungal infections, evidence-based supportive home hygiene and dietary modifications accelerate mucosal healing and prevent recurrence:
- Warm Saline Flushes: Dissolve half a teaspoon of fine salt into one cup of warm water. Swish gently for thirty seconds and spit out three times daily. Saline cleanses raw mucosal surfaces, reduces tissue swelling, and alters local oral pH without irritating inflamed tissue.
- Sodium Bicarbonate (Baking Soda) Rinse: Dissolving half a teaspoon of baking soda in warm water creates a slightly alkaline oral environment that disrupts Candida fungal adherence.
- Probiotic Dietary Support: Consuming unflavored, unsweetened yogurt or kefir containing live Lactobacillus acidophilus cultures replenishes beneficial microflora that compete with Candida for mucosal binding sites. Avoid sugary flavored yogurts, as added sugars fuel fungal metabolism.
- Toothbrush Replacement: Discard your toothbrush immediately upon starting antifungal treatment and replace it with a new ultra-soft bristle brush. Once the infection completely clears, replace the toothbrush a second time to prevent self-re-inoculation.
- Dietary Refined Sugar Reduction: Minimize consumption of sodas, candies, and refined carbohydrate snacks during active treatment to deprive fungal colonies of easily accessible glucose.
Red Flag Warning Signs: When to Seek Urgent Medical Care
In most healthy individuals, oral thrush responds rapidly to treatment within one to two weeks. However, fungal spread beyond the oral cavity signals potential complications requiring immediate physician intervention:
- Difficulty or Pain When Swallowing (Dysphagia/Odynophagia): Severe pain when swallowing or a sensation of food getting stuck behind the breastbone indicates esophageal candidiasis, where the fungal infection has spread down the esophagus. This is an AIDS-defining condition and requires urgent systemic antifungal therapy.
- High Fever and Chills: Oral thrush does not cause high fever. The onset of systemic fever suggests bacterial superinfection or systemic candidemia in vulnerable patients.
- Inability to Drink Fluids: Especially in infants or elderly individuals where severe mouth pain prevents adequate fluid intake, leading to acute dehydration.
- Frequent Unexplained Recurrences: Thrush that returns repeatedly without obvious triggers (like antibiotics or inhalers) warrants a medical workup including fasting blood glucose testing for undiagnosed type 2 diabetes, complete blood count for anemia, and immune panel evaluation.
Frequently Asked Questions
How fast does oral thrush clear with antifungal treatment?
With appropriate prescription antifungal therapy like nystatin oral suspension or fluconazole tablets, symptoms typically begin improving within forty-eight to seventy-two hours, with complete mucosal clearing achieved in seven to fourteen days.
Can I scrape off the white spots caused by oral thrush?
You can gently wipe away the white patches with clean gauze, but doing so exposes an inflamed, bright red, and tender tissue surface underneath that may bleed easily. Avoid aggressive scraping, which damages the mucosal barrier.
What causes oral thrush in healthy adults who do not wear dentures?
In adults without dentures, the most common triggers are a recent course of broad-spectrum antibiotics, use of inhaled steroid medications for asthma without rinsing, undiagnosed high blood sugar, or severe dry mouth.
How can I prevent oral thrush when using a steroid asthma inhaler?
Always use a spacer chamber with metered-dose inhalers to reduce drug deposition in the mouth. Immediately after inhaling, thoroughly rinse your mouth with warm water, gargle, and spit it out into the sink without swallowing.
Is oral thrush contagious through kissing or sharing utensils?
Oral thrush is generally not contagious between healthy adults because Candida is already present in most people's mouths. However, transmission can occur between a breastfeeding mother and infant or to someone with a compromised immune system.
Does mouthwash kill oral thrush yeast?
Standard commercial mouthwashes, especially those containing alcohol, irritate inflamed oral tissues and worsen dry mouth without curing fungal overgrowth. Prescription chlorhexidine gluconate or specific antifungal suspensions should be used instead.
Why must both mother and baby be treated during breastfeeding thrush?
If only the infant or only the mother is treated, the fungal yeast continuously passes back and forth between the baby's mouth and the mother's nipples during feedings, creating an endless cycle of re-infection.
What is the difference between oral thrush and leukoplakia?
Oral thrush lesions can be wiped or scraped away to reveal a raw, bleeding surface underneath. Leukoplakia presents as firm, adherent white patches that cannot be scraped off and requires clinical biopsy to evaluate for premalignant changes.
What are the warning signs of esophageal candidiasis?
Warning signs include painful swallowing, difficulty getting solid foods or liquids down, and a persistent burning ache behind the sternum in the chest. This requires immediate medical evaluation and systemic oral or intravenous antifungals.
